












Now Reading: GLP-1 Diet: What to Eat If You’re on Ozempic or Wegovy (Muscle-Preserving Nutrition)
-
01
GLP-1 Diet: What to Eat If You’re on Ozempic or Wegovy (Muscle-Preserving Nutrition)

GLP-1 Diet: What to Eat If You’re on Ozempic or Wegovy (Muscle-Preserving Nutrition)


GLP-1 medications like Ozempic and Wegovy (semaglutide) work by slowing digestion, quieting appetite signals, and helping you feel full on far less food than before.
That’s exactly why they’re so effective for weight loss — and exactly why what you eat while taking them matters more than it ever did before.
When appetite drops this much, it’s easy to eat too little of the nutrients your body actually needs, especially protein. And when that happens, a meaningful share of the weight you lose isn’t fat — it’s muscle.
This guide breaks down what the research actually shows about muscle loss on GLP-1 medications, how much protein you need, which foods to prioritize, which to limit, and how to manage the gut side effects that make eating well feel harder than it should.
Table of contents
- How GLP-1 Medications Change the Way You Eat
- Do GLP-1 Medications Cause Muscle Loss?
- How Much Protein Do You Need on Ozempic or Wegovy?
- Fiber and Gut-Friendly Foods: Managing Constipation and Bloating
- Healthy Fats — and Why You Shouldn’t Cut Them Out Completely
- Hydration: An Underrated Risk
- Foods to Limit or Avoid on a GLP-1 Diet
- Managing Nausea, Constipation, and Other GI Side Effects
- Protein Alone Isn’t Enough: Why Resistance Training Matters
- Sample Structure for a Muscle-Preserving GLP-1 Day
- When to Talk to Your Doctor About Nutrition
- Frequently Asked Questions
How GLP-1 Medications Change the Way You Eat
Semaglutide and tirzepatide (the active ingredients in Ozempic, Wegovy, Mounjaro, and Zepbound) belong to a class of drugs that mimic a hormone your gut releases naturally after meals. In practice, that means three things happen at once: your stomach empties more slowly, your brain’s hunger signals get turned down, and your blood sugar regulation improves.
The net effect is that most people simply eat less — often much less — without having to think about it. That’s the whole point of the medication. But it also means every meal has to work harder nutritionally, because there are fewer meals and smaller portions to deliver the protein, fiber, vitamins, and minerals your body still needs every day.
Do GLP-1 Medications Cause Muscle Loss?
Yes, to some extent — though it’s important to understand the actual numbers rather than assume the worst.
In a DXA (dual-energy X-ray absorptiometry) substudy of the landmark STEP 1 trial, participants taking semaglutide 2.4 mg lost an average of 19.3% of their total fat mass and 9.7% of their total lean body mass over 68 weeks. Because fat dropped proportionally more than muscle, the percentage of the body made up of lean tissue actually increased slightly over the course of the trial.
A similar pattern showed up with tirzepatide. In a DXA substudy of the SURMOUNT-1 trial, participants lost 21.3% of their body weight, made up of roughly 75% fat mass and 25% lean mass — a ratio researchers describe as consistent with what’s typically seen in other successful weight-loss interventions, including diet-alone and bariatric surgery.
Here’s the catch: 25% of a large weight loss is still a meaningful absolute amount. For someone losing 20 kg (44 lb), around 5 kg (11 lb) of that could be lean tissue. And a smaller study following semaglutide patients for a year (the SEMALEAN study) found lean mass dropped by about 3 kg in the first seven months before stabilizing — with handgrip strength actually improving overall by the one-year mark, suggesting the muscle that remained was functioning well.
The takeaway from all of this research is consistent: some lean mass loss is a normal part of losing a large amount of weight quickly, but the degree to which it happens is not fixed. Protein intake and physical activity are the two levers that determine whether you lose mostly fat with muscle intact, or whether you lose a meaningful amount of both.
How Much Protein Do You Need on Ozempic or Wegovy?
Protein is the single most important nutrition lever for preserving muscle on a GLP-1 medication, and it’s usually the first thing to fall short when appetite drops.
Most obesity medicine specialists and registered dietitians recommend 1.2 to 1.6 grams of protein per kilogram of body weight per day (roughly 0.55–0.73 g per pound) for people actively losing weight on GLP-1 therapy — well above the general adult recommendation of 0.8 g/kg/day. For a person weighing 75 kg (165 lb), that works out to about 90–120 grams of protein daily.
In practical terms, aim for 25–30+ grams of protein per meal, spread across three to four meals or meal-plus-snack combinations rather than one large sitting. This matters because muscle protein synthesis responds better to protein spread evenly through the day than to one big dose at dinner, and because large meals are also the ones most likely to trigger nausea on a GLP-1 medication.
A simple habit that helps: eat your protein source first at each meal, before vegetables or starches, so if you fill up quickly you’ve still gotten the nutrient your muscles need most.
Best Protein Sources for a GLP-1 Diet
- Lean meats: skinless chicken breast, turkey, and lean cuts of beef or pork (roughly 25–30 g protein per 100 g serving)
- Fish and seafood: salmon, tuna, sardines, mackerel, and shrimp — fatty fish also supplies anti-inflammatory omega-3s and is generally easier to tolerate than fried preparations
- Eggs: about 6 g of complete protein per large egg, plus choline and B vitamins; two to three eggs deliver 12–18 g in a small, easy-to-digest volume
- Dairy: Greek yogurt (15–20 g per 170 g serving) and cottage cheese (about 14 g per half cup) provide slow-digesting casein plus probiotics
- Plant-based options: tofu, tempeh, edamame, lentils, and chickpeas — lentils alone provide about 18 g of protein and 15 g of fiber per cooked cup
- Protein shakes or powders: a practical backup for days when appetite is too low for solid food, or for hitting a protein target without added volume
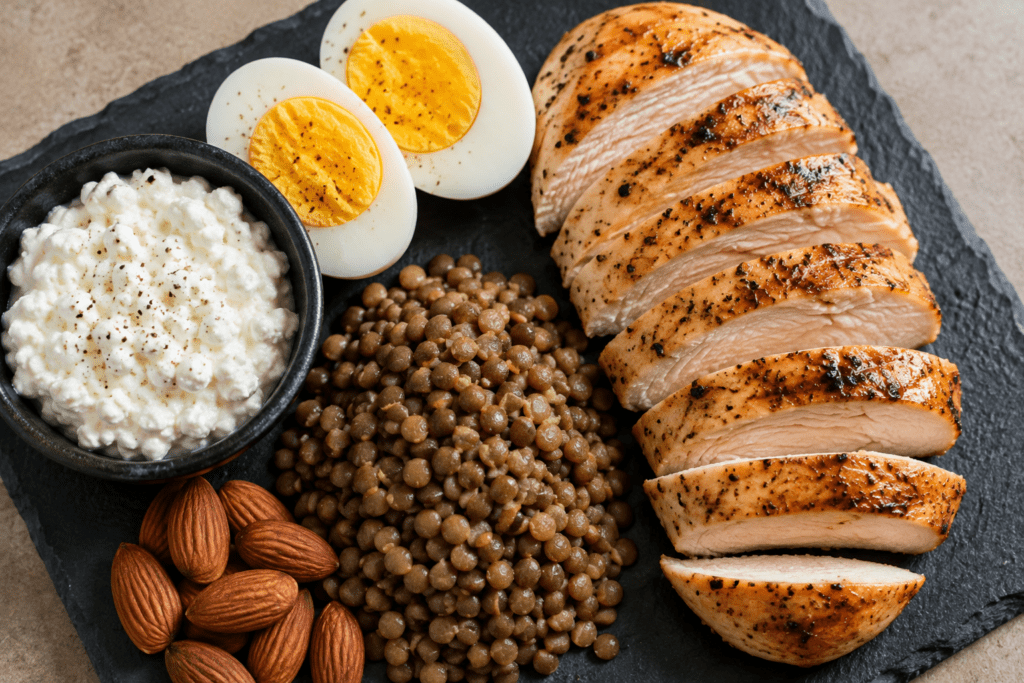
Fiber and Gut-Friendly Foods: Managing Constipation and Bloating
Fiber does double duty on a GLP-1 diet: it supports steady digestion in a gut that’s already moving more slowly, and it’s one of the first things to disappear when total food intake drops, since fibrous foods take up “stomach space” that feels harder to spare.
Prioritize:
- Leafy greens (spinach, kale, arugula) for micronutrients with minimal bulk
- Cruciferous vegetables (broccoli, cauliflower, Brussels sprouts) for fiber and gut motility
- Legumes (lentils, chickpeas, black beans) for combined protein and soluble fiber
- Whole grains (oats, quinoa, brown rice) for steady energy
- Fermented foods (kimchi, sauerkraut, kefir, miso) — a 2021 Stanford study published in Cell found that a diet higher in fermented foods increased gut microbiome diversity and lowered inflammation markers over a 10-week period, which may help offset the reduced dietary variety that often comes with eating less overall
One important nuance: if you’re increasing fiber intake, do it gradually. A sudden jump in fiber on top of already-slowed digestion can worsen bloating and gas rather than relieve it. Cooked vegetables also tend to be better tolerated than raw ones in the first few weeks of treatment.
Healthy Fats — and Why You Shouldn’t Cut Them Out Completely
It’s tempting to go very low-fat on a GLP-1 medication, since fatty foods are the most common trigger for nausea. But cutting fat too aggressively can backfire in an unexpected way: your gallbladder needs dietary fat to contract and empty bile regularly. When fat intake drops too low for too long, bile can sit and thicken, which is itself a risk factor for gallstones — a documented, though modest, risk of rapid weight loss with or without GLP-1 medications.
The goal isn’t to avoid fat, but to keep it moderate and spread across meals rather than concentrated in one large, greasy dish.
Good sources in small, deliberate portions:
- Avocado (about 5 g monounsaturated fat and 2.5 g fiber per quarter avocado)
- Extra virgin olive oil, a tablespoon over vegetables
- Nuts, roughly a small handful (about 20–23 almonds)
- Fatty fish, which pulls double duty as a protein source
Hydration: An Underrated Risk
Dehydration is one of the more overlooked complications of GLP-1 therapy. Eating less means less water from food, and nausea can further reduce how much people want to drink. Sip water consistently through the day rather than trying to catch up with large volumes at once, and lean on hydrating foods when plain water feels unappealing:
- Cucumber (about 96% water)
- Watermelon (about 92% water)
- Bone broth, which also supplies electrolytes, collagen, and a small amount of protein — useful on days when nausea makes solid food unappealing
Foods to Limit or Avoid on a GLP-1 Diet
Certain foods reliably make GLP-1 side effects worse or crowd out more valuable nutrition from an already-reduced daily intake.
- Fried and greasy foods — fat is naturally slow to digest, and on top of a medication that already delays gastric emptying, greasy meals are the most common trigger for nausea and vomiting
- Sugary drinks and sweets — sodas, juices, and pastries spike blood sugar and use up limited stomach capacity without delivering useful nutrients
- Carbonated drinks — including sparkling water, which can worsen bloating and the sense of fullness that already comes on fast
- Ultra-processed snacks — chips, packaged pastries, and similar foods are calorie-dense but nutrient-poor at a time when every bite needs to count
- Alcohol — many people report feeling its effects more strongly on a GLP-1 medication, and it adds empty calories, irritates the gut lining, and can worsen both nausea and dehydration; general guidance is no more than one drink daily for women and two for men, in consultation with your prescriber
- Very large meals — even healthy food in too large a portion can overwhelm a slower-moving digestive system; smaller, more frequent meals (roughly 200–400 calories each) tend to be much better tolerated than two or three big ones
Managing Nausea, Constipation, and Other GI Side Effects
Gastrointestinal side effects are the most commonly reported issue with GLP-1 medications, and diet plays a large role in how mild or severe they feel. In the STEP 1 trial, nausea occurred in roughly 44% of semaglutide patients versus 18% on placebo, and constipation in about 24% of semaglutide patients. Similar patterns show up with tirzepatide, where meta-analyses report nausea around 20%, constipation around 7–12%, and vomiting around 9%.
What tends to help:
- For nausea: bland, low-fat, easily digestible foods — crackers, plain rice, boiled potatoes, ginger tea, and bone broth. Eating slowly and stopping at the first sign of fullness, rather than waiting for the usual “full” feeling, prevents a lot of discomfort.
- For constipation: gradual increases in fiber (soluble fiber from legumes and oats in particular), plus consistent water intake and light physical activity like walking, which supports gut motility.
- For bloating: smaller meals, avoiding carbonated drinks, and introducing fermented foods slowly rather than all at once.
If side effects are severe or persistent, that’s a conversation for your prescribing doctor — dose adjustments are common and effective, and side effects generally ease within the first several weeks of treatment or after a dose change.
Protein Alone Isn’t Enough: Why Resistance Training Matters
Diet is only half of muscle preservation. Multiple studies on GLP-1 therapy point to the same conclusion: protein without a training stimulus helps, but it isn’t as effective as protein combined with resistance exercise. One prospective study following patients who combined structured resistance training with adequate protein intake found they lost roughly 13% of body weight but only about 3% of muscle mass over six months — a far more favorable ratio than typically seen with medication alone.
General guidance for people on GLP-1 therapy is two to three resistance-training sessions per week targeting major muscle groups, with gradual increases in resistance over time. This doesn’t need to mean a gym membership — bodyweight exercises, resistance bands, and basic compound movements (squats, rows, presses) are enough to provide the stimulus that, paired with adequate protein, helps the body hold onto lean tissue while fat comes off.
Sample Structure for a Muscle-Preserving GLP-1 Day
This isn’t a rigid meal plan, but a template for spacing protein and nutrients across a lower-volume day:
- Breakfast: 2–3 eggs or a Greek yogurt bowl with berries (12–20 g protein)
- Mid-morning (if needed): a small protein shake or a handful of nuts
- Lunch: grilled chicken or salmon with a cooked vegetable and a small serving of quinoa or lentils (25–30 g protein)
- Afternoon: cottage cheese with fruit, or a hard-boiled egg
- Dinner: lean protein with non-starchy vegetables and a moderate portion of healthy fat (25–30 g protein)
- Throughout the day: water sipped consistently, plus a hydrating food like cucumber or bone broth if appetite is very low
When to Talk to Your Doctor About Nutrition
Most people can manage well with the strategies above, but certain signs point to a need for closer medical support:
- Persistent fatigue, noticeable weakness, or hair thinning
- Weight loss significantly faster than your doctor expects (as a general guide, more than about 2 lb/week is worth flagging)
- Ongoing inability to tolerate solid food
- A history of gallstones, or new sharp, localized upper-right abdominal pain (a possible sign of gallbladder involvement, distinct from typical GLP-1 nausea)
Bloodwork checking protein markers, vitamin D, iron, B12, and folate can catch nutritional gaps early. A referral to a registered dietitian is especially useful for people who struggle to hit protein targets, have a condition like kidney disease that changes protein needs, or simply want a structured, personalized plan.
Frequently Asked Questions
How much protein should I eat per day on Ozempic or Wegovy?
Most experts recommend 1.2 to 1.6 grams of protein per kilogram of body weight daily for people actively losing weight on a GLP-1 medication — for a 75 kg (165 lb) person, that’s about 90–120 grams a day, spread across three to four meals.
Will I definitely lose muscle on a GLP-1 medication?
Some lean mass loss is common and expected during any significant weight loss, GLP-1 or otherwise.
Clinical trial data shows roughly 25% of total weight lost on these medications comes from lean tissue, with the rest from fat. Adequate protein and resistance training are the two factors shown to shift that ratio in your favor.
What foods help with nausea on GLP-1 injections?
Bland, low-fat foods like crackers, plain rice, boiled potatoes, and ginger tea tend to be best tolerated, especially in the 24–72 hours after an injection. Eating slowly, in smaller portions, and avoiding fried or strong-smelling foods during that window helps significantly.
Can I drink alcohol while on Ozempic or Wegovy?
It’s best to limit alcohol significantly. Many people find they’re more sensitive to its effects on a GLP-1 medication, and it can worsen nausea, contribute to dehydration, and add calories that displace more useful nutrition.
Talk to your prescriber about what’s appropriate for you.
Do I need to take supplements on a GLP-1 diet?
Not automatically, but a general multivitamin can help cover gaps when total food intake is significantly reduced. Vitamin D, B12, iron, and omega-3s are worth discussing with your doctor, ideally guided by bloodwork rather than guesswork.
Is a low-carb diet safe to combine with a GLP-1 medication?
Moderate carb reduction is generally fine, but very low-carb or ketogenic approaches need medical supervision — combining extreme carb restriction with a medication that already suppresses appetite can push total calorie and nutrient intake dangerously low.
This article is for general educational purposes and is not a substitute for personalized medical advice. Talk to your prescribing doctor or a registered dietitian about the nutrition plan that’s right for you.
Related Posts


Stay Informed With the Latest & Most Important News
Previous Post
Next Post










Advertisement